
SCIENCE / VOLUME 03FORMULATION · DELIVERY · CLINICAL

The physics of
a 15 µm layer.

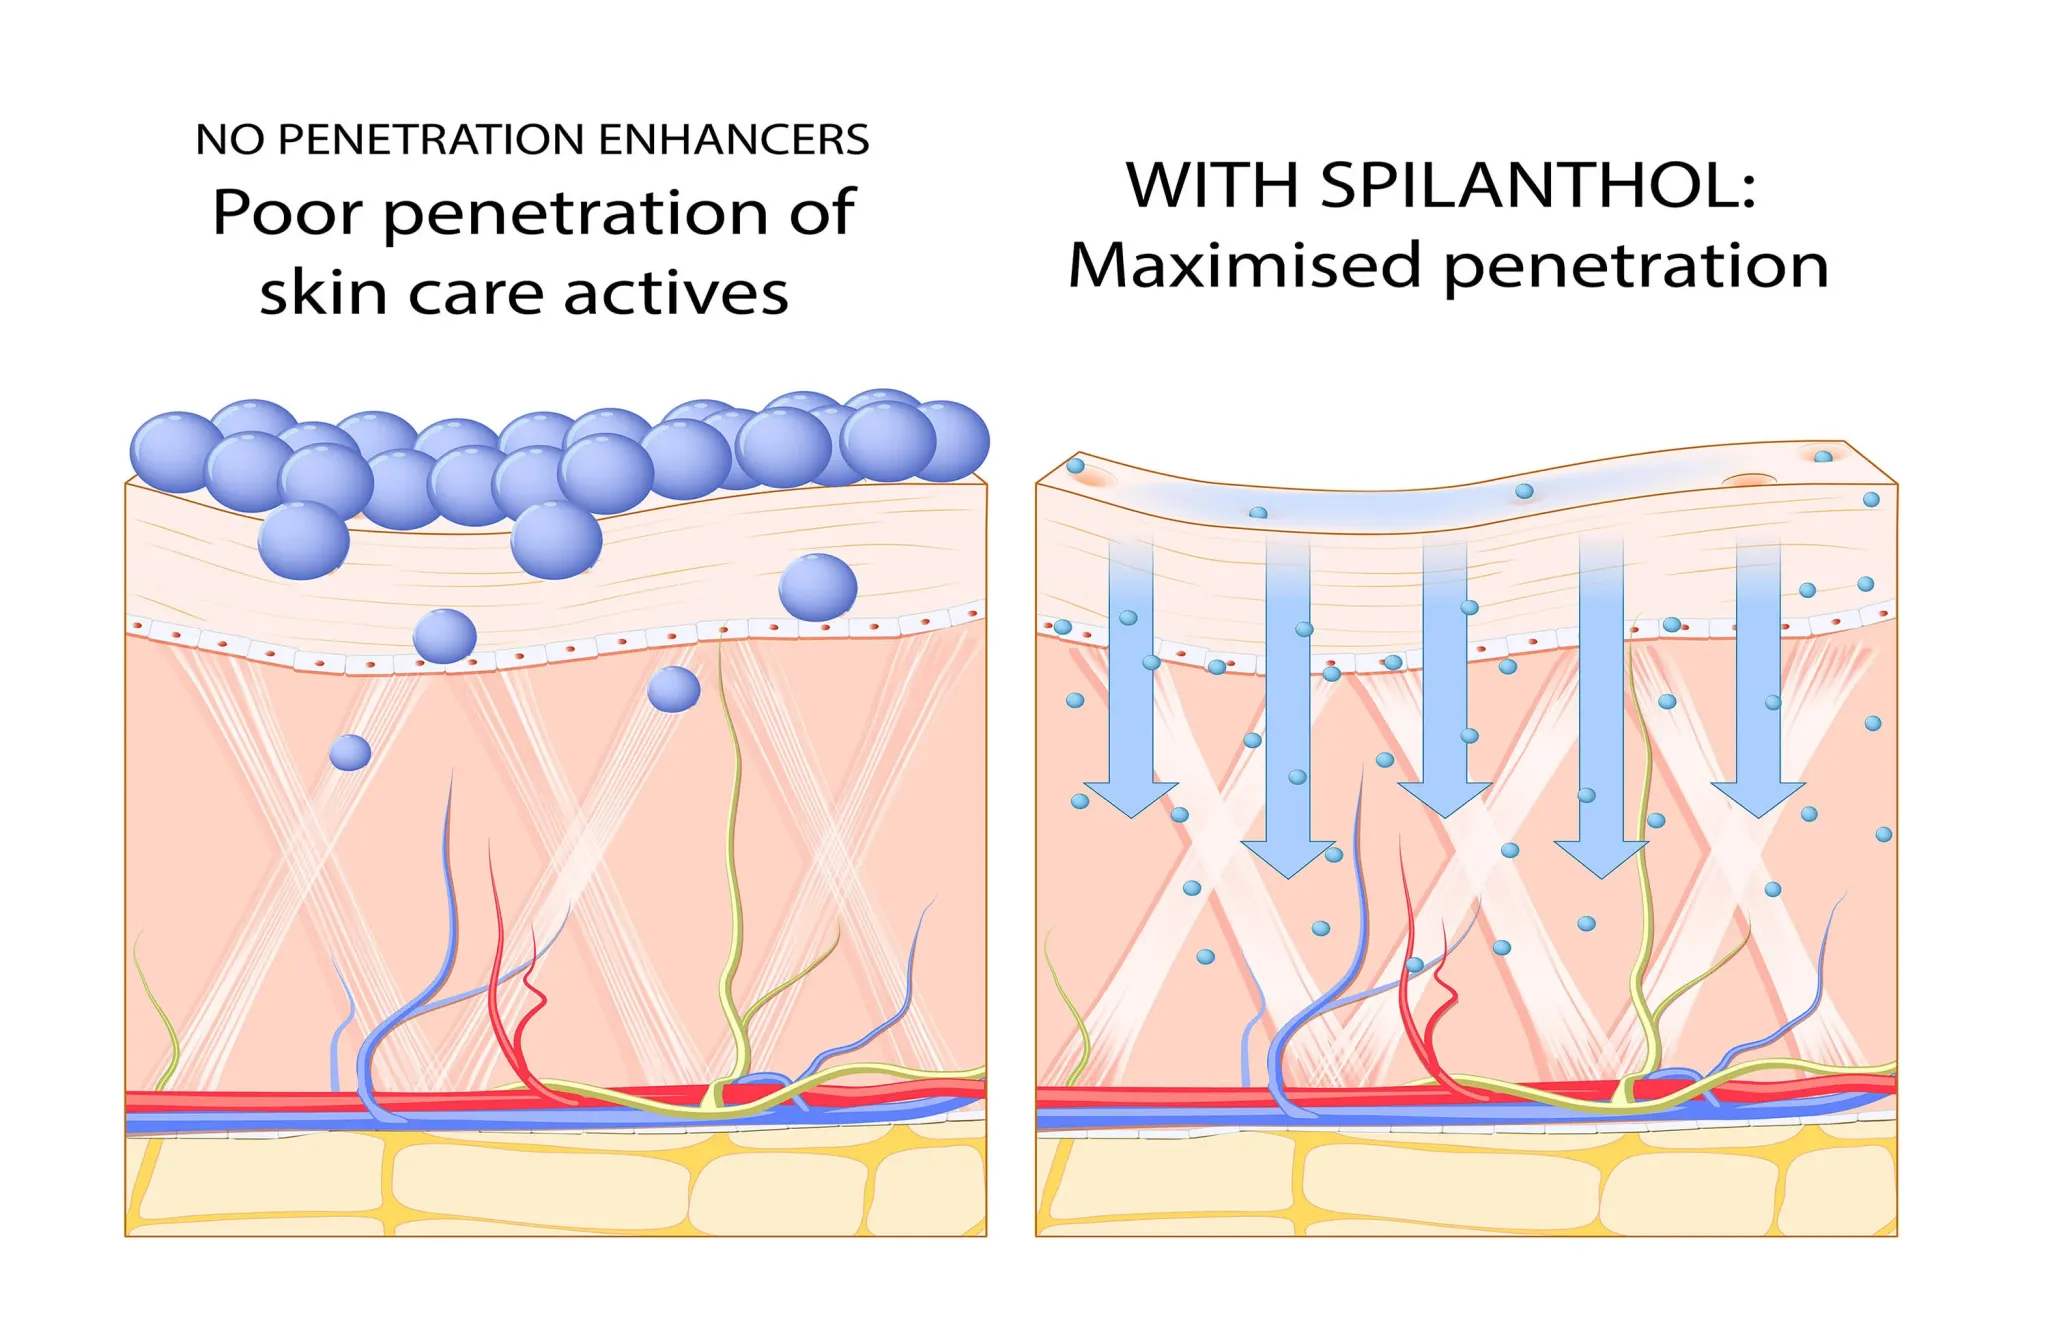
The stratum corneum is roughly the thickness of a red blood cell — a 15-micron mosaic of dead corneocytes stacked in a lipid matrix. It is the reason topical medicine is difficult. YUTAN uses this kind of formulation and pharmacology literacy to evaluate, explain and operate science-led brands across dermatology and OTC markets.

Six vehicles
for one problem.

VH · 001 · FOAM
ACTIVE
FIG. 01
DENSITY
0.04g/mL
COLLAPSE
45s

Fast-breaking foams

Low-density hydro-alcoholic vehicles that spread thinly across scalp, collapse in under a minute, and leave a uniform residue without occlusion or greasiness.

Engineered for the infundibular region of the hair follicle, this transient low-density hydro-alcoholic bubble matrix collapses spontaneously within 45 seconds upon contact with skin at 37°C. The collapse drives the active ingredient into a supersaturated micro-film, powerfully enhancing transmembrane flux without relying on irritant chemical penetration enhancers such as propylene glycol — and without any greasy residue.
VH · 002 · GEL-P
ACTIVE
FIG. 02
FILM t
168h
RELEASE
0-order

Polymer film gels

Single-application gels that cure into a transparent film, releasing an active in near-zero-order kinetics over a full week. One dose, seven days of work.

A single application undergoes rapid phase inversion driven by volatile solvent evaporation, curing into an invisible, water-resistant, semi-permeable polymer film. This film network functions as a constant-rate reservoir, maintaining a steady chemical potential gradient and delivering the active pharmaceutical ingredient via near-zero-order kinetics continuously for seven days.

VH · 003 · SPRAY
ACTIVE
FIG. 03
ONSET
5-15min
IELT Δ
+3.4×

Eutectic sprays

Two-active spray systems using melting-point depression to reach mucosal nerve endings within minutes — precise dosing without excessive numbness or alcohol sting.

By precisely engineering the binary phase diagram of two crystalline actives, their eutectic melting temperature is depressed below the surface temperature of the skin. The resulting liquid eutectic system possesses extremely high thermodynamic activity (a=1), enabling efficient penetration through the mucosal layer to reach nerve endings within minutes — entirely without the stinging sensation associated with high-concentration alcohol.

VH · 004 · CREAM-D
ACTIVE
t=0 t=12wk
FIG. 04
MELANIN Δ
-42%
DURATION
8-12wk

Depigmenting creams

Hydrolytically-stable emulsions carrying tyrosinase inhibitors, retinoids and corticosteroids — the pigment ladder from monotherapy to FHT triple combination.

Purpose-built to conquer the incompatibility and hydrolytic instability of multi-component actives — retinoids, hydroquinone, and corticosteroids — within a single formulation. At the microscopic level, a spatially compartmentalized multi-phasic liquid-crystalline lipid network closely mimics the intercellular lipid matrix, simultaneously preventing water loss and oxidative degradation while enabling sequential, layer-by-layer release along the pigment ladder.

VH · 005 · LACQUER
ACTIVE
NAIL PLATE · SUSTAINED RELEASE
FIG. 05
ADHESION
7days
PENETR.
92%

Medicated lacquers

Water-resistant film-forming lacquers that adhere to the nail plate for a full week, releasing amorolfine into the nail bed while resisting daily washing.

An amphiphilic polymer matrix formulation that bonds tightly to the highly hydrophilic keratin of the nail plate. Upon solvent evaporation, a highly occlusive local microenvironment is established, promoting full hydration of the nail plate and dramatically increasing the porous diffusion coefficient — driving active drug transport across the nail plate deep into the nail bed.

VH · 006 · GEL-H
ACTIVE
CHONDROITIN — SULFATE — WATER
FIG. 06
MW
>500Da
HYDR. Δ
+38%

Heparinoid gels

MPS-anchored polysaccharide gels. Densely-sulphated backbones hydrogen-bond water into the outer dermis and stimulate endogenous hyaluronate synthesis.

Built on a semi-synthetic glycosaminoglycan — mucopolysaccharide polysulfate (MPS). Leveraging the strong negative charge carried by its densely sulphated backbone, it anchors water molecules within the extracellular matrix via hydrogen bonding, while simultaneously triggering comprehensive endogenous hyaluronic acid synthesis in the deeper epidermis.

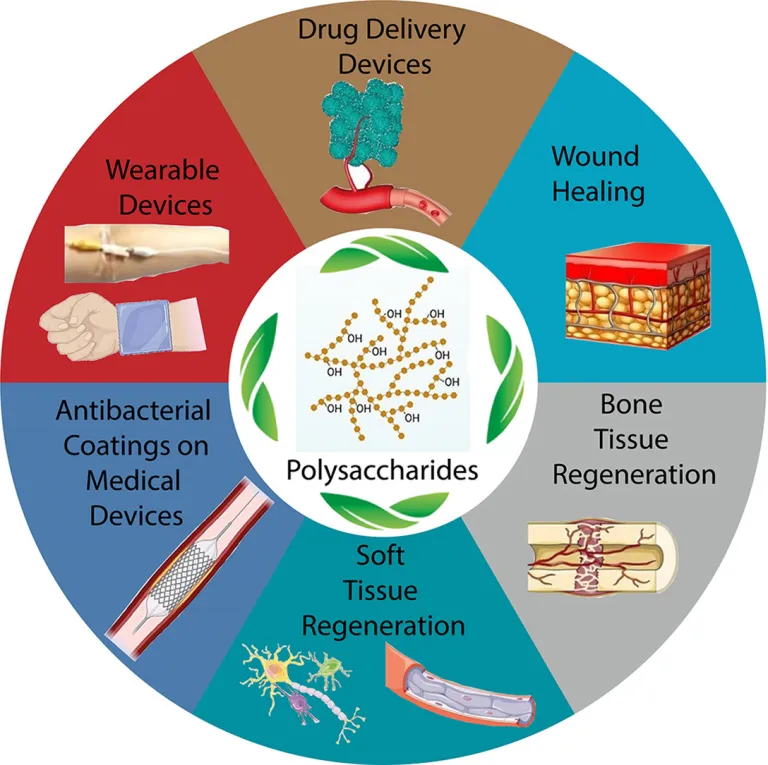
§ 03  —  POLYSACCHARIDES

The molecule that taught skin
how to hold water.

Mucopolysaccharide polysulfate is a semi-synthetic glycosaminoglycan built from polysulfated chondroitin. It has been used clinically for over five decades — for bruises, superficial thrombophlebitis, xerosis, atopic dermatitis and post-inflammatory dryness — and it is the pharmacological backbone of Hirudiox®.

MPS hydration study
CORE MECHANISMS & BIOLOGICAL ACTIVITY

Four pathways, one molecule.

Mucopolysaccharide polysulfate is not a single-action molecule. Its densely-sulphated glycosaminoglycan backbone interacts with multiple dermal systems at once — coagulation, inflammation, hydration and vascular function.

01 · ANTITHROMBOTIC & FIBRINOLYTIC
Exhibits heparin-like activity, interacting with blood coagulation factors and releasing Tissue Factor Pathway Inhibitor (TFPI) to prevent and dissolve superficial blood clots.
02 · ANTI-INFLAMMATORY
Helps rapidly resolve subcutaneous hematomas, infiltrates, and acute inflammation in superficial vascular dermal tissues.
03 · DERMAL HYDRATION
Stimulates endogenous hyaluronate synthesis, increasing the water-binding capacity, structural density, and elasticity of the extracellular matrix.
04 · VASCULAR ACTION
Promotes microvascular blood flow and strengthens the epidermal barrier by modulating tight junction proteins inside dermal papillary loops.
STUDY 002 · CUTANEOUS BLOOD FLOW

Why the dermis notices

Cutaneous blood flow (CBF) is regulated through dermal papillary loops — arterial capillaries that supply nutrients and clear metabolites. When CBF is impaired, so is thermoregulation, wound healing, and the skin's response to injury.

Laser-Doppler studies show that topically-applied MPS increases local skin blood volume and basal sweating — evidence that a molecule >500 Da can, in fact, reach the dermis and act on its cells. Clinical data demonstrate that, despite MPS exceeding 500 Da in molecular weight, topical administration via a specialised vehicle enables efficient penetration through compromised or xerotic barrier-deficient regions, increasing basal capillary blood flow in the local dermis by 1.9× and accelerating haematoma resolution and deep scar remodelling.

This is why MPS-containing topicals are clinically effective for conditions rooted in vessel-function failure: bruising, superficial thrombophlebitis, asteatosis, chronic venous discomfort, and the ageing skin's slow retreat from its own microcirculation.

Cutaneous blood flow study
50+ yr
Cumulative clinical use
+38%
Hydration Δ vs. baseline · 4 wk
1.9×
Local cutaneous blood volume
>500 Da
Molecular weight, dermal-reaching
§ 03  —  FOAMS

Why foam wins
on the scalp.

Xcare Minoxidil 5% Cutaneous Foam

A solution poured onto scalp will run off. A cream will smear the hair and refuse to reach the follicle. A fast-breaking foam — a low-viscosity liquid that expands into a bubble matrix on contact with warmth, then collapses in 30–60 seconds — solves both problems at once.

Foam permeation depends on three physical parameters: surface tension, evaporation kinetics, and the diffusion coefficient of the active in the residue phase. In our proprietary Xcare vehicle, these three are tuned so that minoxidil precipitates as a supersaturated film on the scalp. Upon contact with scalp warmth, the bubble matrix collapses precisely within 30–60 seconds, driving minoxidil to precipitate across the stratum corneum with exceptionally high thermodynamic driving force — a driving force that pushes molecules through the corneum without the propylene glycol that irritates so many patients. This not only eliminates the risk of contact dermatitis but also substantially improves daily patient adherence.

The clinical consequence is unglamorous but important: patients actually apply it. In the pharmacology of hair loss, adherence is half the battle, and vehicle design is where that battle is won.

↳ See Xcare foam · Products
§ 04  —  LITERATURE

What the journals say.

NAT REV DIS PRIMERS
Androgenetic alopecia — a comprehensive review
A read-through of the 2025 primer: genetics, DHT signalling and the therapeutic landscape.
A genetic predisposition renders scalp follicles sensitive to dihydrotestosterone, which shortens the growth phase and miniaturises the shaft over successive cycles. The ranking has not changed — topical minoxidil and oral or topical finasteride remain the two best-evidenced interventions — but the emphasis has: adherence and early intervention now matter more than the choice between them, and topical delivery is complementary to systemic therapy, not its rival.
2025 →
J AM ACAD DERMATOL
Consensus on melasma diagnosis & treatment
Reframing melasma as a chronic, relapsing dermatosis of the pigment system.
Melasma is not surface pigment but a chronic disease of the pigment system: hyperactive melanocytes transferring more pigment, pigment dropped into the dermis, an abnormal increase in local blood vessels and a damaged basement membrane — which is why it relapses. Management follows three principles: photoprotection that covers visible light, staged depigmentation with hydroquinone and a triple combination for moderate-to-severe disease, and gentler agents for long-term maintenance. It is controlled, not cured, and visible improvement takes eight to twelve weeks.
2025 →
BR J DERMATOL
Topical finasteride vs. oral — a systematic review
Comparable hair-count gains and local DHT reduction, with markedly smaller serum suppression.
A systematic review of the topical-versus-oral trials reported comparable improvements in hair count and comparable reductions in scalp DHT, with serum DHT suppression markedly smaller than with oral dosing. The local pharmacology is preserved and the systemic footprint shrinks. Trials varied in vehicle, concentration and duration, and the review calls for longer studies — which is why we read it as a design brief rather than a final answer.
2024 →
SKIN PHARM PHYSIOL
Mucopolysaccharide polysulfate — five decades of clinical evidence
A heparinoid in continuous clinical use since the 1960s: hydration, inflammation, microcirculation.
A semi-synthetic glycosaminoglycan whose sulphate density binds and holds water in the outer dermis, restoring the viscoelasticity that dry, photo-aged skin loses and apparently coaxing the skin into making more of its own hyaluronate. Despite a molecular weight above 500 daltons, laser-Doppler studies keep showing it raises local skin blood volume. Three jobs at once: hydrate, calm inflammation, and improve microcirculation.
2023 →
J DRUGS DERMATOL
Single-application terbinafine — pharmacokinetics of a film-forming vehicle
One application, roughly thirteen days of drug retained in the stratum corneum.
Terbinafine is fungicidal and highly lipophilic, so it partitions into and stays within the lipid-rich stratum corneum. A single application of a film-forming gel leaves a polymer film that acts as a depot, releasing the drug steadily at fungicidal concentrations — published pharmacokinetic work puts that at around thirteen days. The regimen collapses into one supervised event, which is the point: the failure mode is behavioural, not pharmacological.
2022 →
DERMATOL THER
Onion extract + heparin + allantoin gel — scar remodelling evidence
Onion extract, heparin and allantoin — and why timing is the active ingredient.
Combination gels of onion extract, heparin and allantoin act on several levers at once: anti-inflammatory and antiproliferative effects on fibroblasts, softening and hydration of the collagen matrix, and a keratolytic humectant that keeps the scar supple. Data across surgical, burn and post-acne populations consistently favour early, sustained application — starting once the wound has closed and continuing for weeks to months. Low-risk and well tolerated, which is why it belongs in a routine post-operative protocol.
2023 →
Read all evidence notes in the Journal →
